Claims processed to date:12,960,971

Drug units and step-therapy denials cost rheumatology practices recoverable revenue every day.

Rheumatology runs on high-cost biologic infusions, the initial, sequential, and additional-hour administration hierarchy, and step-therapy documentation, where a single J-code, wastage modifier, or missing auth wipes out a high-dollar claim. Manual billing teams catch a fraction of the errors. Ember catches all of them.
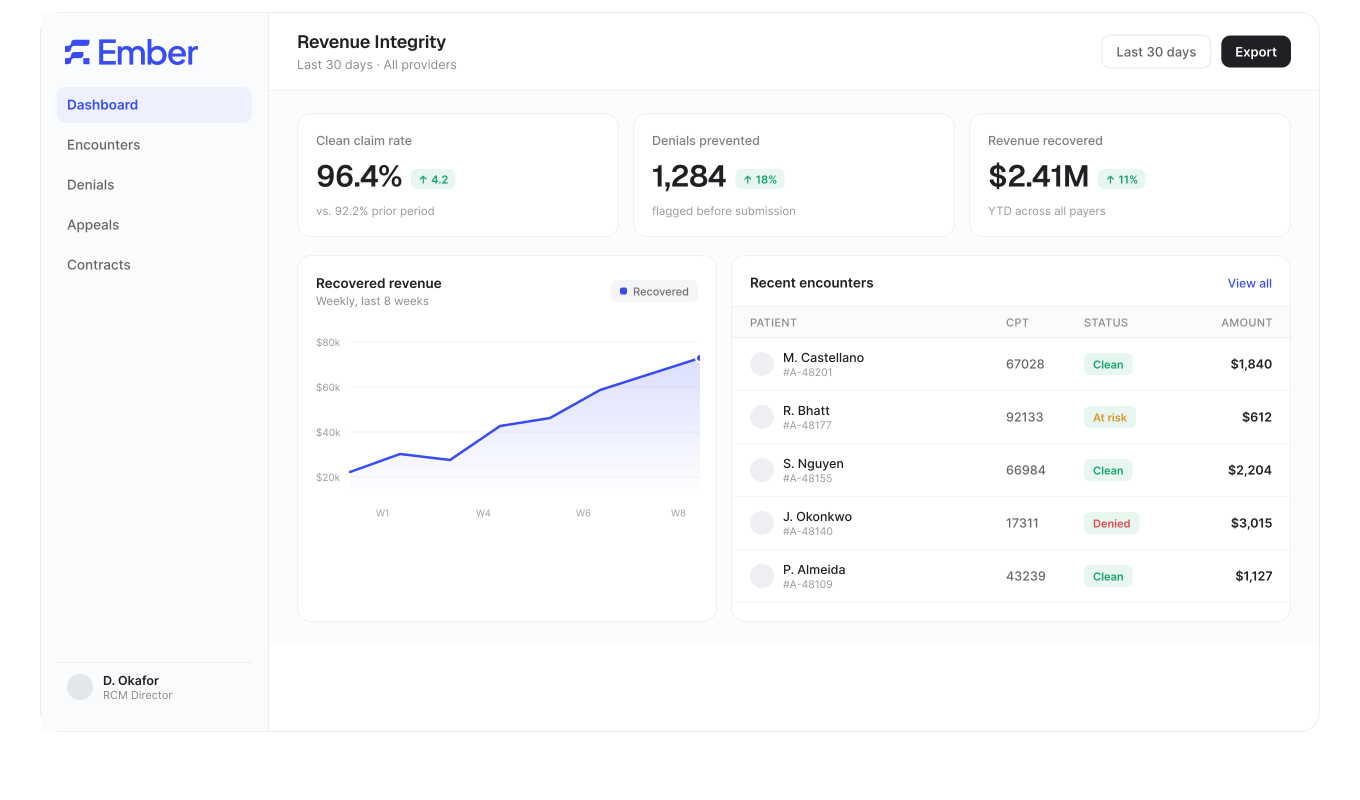
Ember revenue integrity dashboard

2,700+ providers across 40+ states trust Ember AI

Where rheumatology revenue leaks

The denial patterns Ember was built for

Rheumatology runs high-cost biologic drugs, complex infusion administration, and step-therapy scrutiny side by side, and each line has its own denial trap. Drug units, infusion sequencing, and auth gaps compound into systematic underpayment. Ember closes each gap.

01 · Biologic drug units & wastage

J-code, unit, and wastage errors on high-cost infliximab and rituximab.

Infliximab, rituximab, and other biologics carry high per-dose cost, and the smallest J-code, unit, or wastage-modifier error becomes a denial or takeback on an expensive claim. Buy-and-bill margins disappear when JW and JZ modifiers don't match the documented dose. Ember validates units and documented wastage before the drug is billed.

J1745 · J9312 · J3357 · JW · JZ

02 · Infusion administration hierarchy

Initial, sequential, and additional-hour codes miscoded against documented times.

Infusion administration follows a strict initial, sequential, and additional-hour hierarchy tied to documented start and stop times. When those codes are missed or transposed, a full infusion collapses into a partial payment. Ember maps the documented times to the correct administration codes before submission.

96413 · 96415 · 96361 · 96417

03 · Prior auth & step therapy

Auth and documentation denials on biologics requiring failed DMARDs.

Payers require documented step therapy and failed conventional DMARDs before approving biologics, and auth obtained doesn't always match the payer's current policy. Documentation gaps trigger denials on high-value drug claims. Ember flags the missing criteria before the service and builds the appeal package when denials occur.

J1745 · J1602 · 96413 · L38246

Three engines.
One source of truth.

Ember connects clinical documentation, payer policy, and contract terms into a single intelligence layer. Built for the buy-and-bill, infusion-hierarchy, and step-therapy mix rheumatology billing spans every day.

M. Delgado

Encounter #R-61207

Unified
Documentation
Infliximab infusion + admin
Coding
J174596413M05.79
Payer policy
UHC · Biologic infusion
Contract
Rate §4.7

01 · Foundation

Data Engine

Bridges the clinical and the financial. Unifies documentation, coding decisions, payer policy, and contracts across every encounter and provider.

Audit#R-61207
96413Initial infusion, 1 hr
Pass
J1745Infliximab, JZ wastage missing
Flag

Append modifier JZ — zero drug wastage

CMS JW/JZ policy · confidence 0.96

02 · Audit

Coding Engine

Reviews 100% of encounters against national standards, payer-specific policies, your internal guidelines, and your payer contracts. Every flag carries a rule citation.

Re: Claim #R-61207 · Denial CO-50

Infliximab meets medical-necessity criteria under LCD L38246: documented active rheumatoid arthritis and failed conventional DMARDs, per contract §4.7…

Denial received
Appeal drafted
Submitted · in review
Adjudication pending

03 · Recovery

Appeal Engine

Reads CARC and RARC codes, identifies the applicable LCD/NCD policy and contract terms, drafts the appeal letter, packages documentation, and tracks every claim to adjudication.

Audit upstream.
Appeal downstream.

Two workflows do most of the work for rheumatology practices. The first prevents denials before they happen. The second recovers the ones that slip through.

Catch the drug-unit and infusion issue before the claim leaves.

Ember reviews every encounter against coding standards, payer drug and infusion policy, and your contracts. Drug-unit and wastage gaps, infusion-sequencing errors, and step-therapy issues are flagged before submission.

  • 1

    Ingest the encounter

    Pulls infusion records, drug administration logs, procedure codes, and start/stop times from your EHR and practice management system.

  • 2

    Validate against rules

    Checks biologic drug units and wastage, the initial/sequential/additional-hour infusion hierarchy, step-therapy and prior-auth status, and medical-necessity criteria against each payer's specific policies.

  • 3

    Recommend with citation

    Returns the suggested correction tied to the exact payer policy, JW/JZ rule, or contract term.

  • 4

    Educate the provider

    Coding patterns drive provider-level coaching, so infusion documentation and drug charge capture improve across every clinician.

Encounter review#R-61207
96413Initial infusion, 1 hr
Pass
J1745Infliximab, wastage not documented
Flag
96415Additional hour, not documented
Flag

Add JZ + 96415 — zero wastage, additional infusion hour

CMS JW/JZ policy · confidence 0.97

Clean-claim rate
+23%
Encounters reviewed
100%
Net collection rate
+5%

Pull. Review. Push.

When a denial occurs, Ember identifies the root cause, retrieves infusion records, drug administration logs, and step-therapy documentation, references payer policy and contract terms, drafts the appeal, and tracks it through adjudication.

Pull13
CO-50

Medical necessity

CO-16

Units / wastage

Review8
CO-97

Infusion bundling

Push10
CO-B15

Drug auth / step therapy not on file

Learn—
PAID

Biologic appeal

Denial rate
-57%
Cost to collect
-45%
Net revenue per appt
+9.3%

The full revenue cycle

From eligibility to adjudication. Covered.

Audit and appeals are the workhorses, but Ember protects rheumatology revenue at every stage of the cycle.

Eligibility Verification

Confirms active coverage and drug and infusion benefit structure before the visit, and flags buy-and-bill coverage gaps before they become billing problems.

Prior Authorization

Checks auth requirements in real time for biologics and confirms documented step therapy and failed conventional DMARDs, generates medical-necessity documentation, and submits to payer portals automatically.

AI Medical Coding

Reviews 100% of encounters, biologic drug units and wastage and the initial/sequential/additional-hour infusion hierarchy, against national standards and payer rules before claims submit.

Pre-bill Audit

Predicts and prevents denials before claims go out, catching drug-unit and wastage gaps, infusion-sequencing errors, and step-therapy issues before they generate write-offs.

Denial Management

Full appeal lifecycle for every rheumatology denial type, step-therapy dispute, medical necessity, drug auth failure, and units/wastage error, tracked to adjudication.

Underpayment Recovery

Parses contracts to model what each biologic and infusion claim should pay, then surfaces line-item underpayments on high-cost drug claims at scale.

High-dollar biologic revenue, recovered

-57%

denial rate

-45%

cost to collect

100%

encounters audited

7 days

to first results

Based on Ember AI benchmarks across customer practices. Results vary by payer mix and specialty.

Revenue leaders, on the record

What specialty practices and health systems say after putting Ember into production.

“Ember delivered exactly what they promised, and they keep delivering. Providers are able to fit Ember into their daily workflow without it feeling heavy or complicated.”

Katie Greiner

VP of Physician Engagement, Midwest Vision Partners

Missed revenue uncovered
$1M+
Encounters reviewed
200K+
From deployment
3 months
“We looked at a number of AI partners, but Ember stood out because it could identify opportunities for accuracy improvement in our coding and documentation that we might otherwise miss. Ember helps us understand what's missing and why it matters, so we can strengthen our documentation, make our charts more precise and address issues before they impact revenue.”

Kashonna Morrison

VP of Revenue Cycle, Elevate ENT Partners

“Denials can become a significant drain on our team's time, especially when there's a large volume of cases to work through. Ember helps us work through that volume more efficiently and prioritize the cases that need attention. It means our team can spend less time on manual follow-up and more time getting claims resolved.”

Samantha Martin

RCM Billing Manager, Direct Orthopedic Care

“At Bone and Joint Institute of Tennessee, one of my biggest priorities as CEO is ensuring we receive appropriate reimbursement for the care we deliver without administrative costs rising at the same pace as patient volume. Ember AI has helped us reduce our surgical coding costs by 80% while maintaining accuracy, and providing a clear root cause and resolution path for 100% of claims reviewed. This gives our team actionable insights to resolve denials more efficiently.”

John B. Reynolds

CEO, Bone and Joint Institute of Tennessee

“One of the biggest challenges in revenue cycle management is having the visibility to understand where revenue opportunities exist and where reimbursement may be falling short. Having better data and insights allows us to be more proactive, make informed decisions, and identify opportunities to strengthen our financial performance.”

Catherine Roman

Senior Director, Platinum Dermatology Partners

Frequently asked questions

Everything you need to know about how Ember fits into your revenue cycle.

Yes. Ember AI connects seamlessly with all major EHRs and PMS platforms, including Epic, Oracle Cerner, athenahealth, and eClinicalWorks, as well as payer portals. Our standards-based integrations automate prior authorization, eligibility verification, and claims submission, allowing you to preserve existing infrastructure while modernizing the revenue cycle.

See what your rheumatology practice is leaving on the table

Bring us 30 days of denial data. We'll show you where the revenue is and exactly how Ember would recover it.











